Understand the benefit. Document the need.
SMC-L: Aid & Attendance Compensation
Special Monthly Compensation level L is the entry tier of the SMC ladder for veterans who need regular aid and attendance, are permanently bedridden, have lost the use of both feet or one hand and one foot, or are legally blind. Authority: 38 USC § 1114(l), implemented at 38 CFR § 3.350(b) and defined at 38 CFR § 3.352(a).
Find the part that matters to you
Five paths. Start with yours.
Different circumstances. Different evidence. Choose a path to read the criteria, not to receive an eligibility decision.

Help with everyday life
Personal care, eating, dressing, or protection from daily hazards because of service-connected disabilities.
Aid & attendance criteria
Required to remain in bed
Understand the standard and the distinction from prescribed rest.
Read this path
Loss or loss of use
The functional standard for both feet, not a diagnosis by itself.
Read this path
One hand and one foot
The combined loss or loss-of-use route and what it requires.
Read this path
Severe vision loss
The 5/200 threshold and the importance of clinical measurements.
Read this pathThe SMC-L standard is not a percentage you must reach first. The qualifying need must come from service-connected disabilities.
Read the TDIU & under-100% guidance
Make the need
visible in the record.
From daily life to supporting evidence
Show the help you need.
And why you need it.
A form, a clinical finding, and a caregiver's account each tell part of the story. Connect the daily limitation to the service-connected condition.
The complete reference
The details behind each path.
All of the guidance is here. Open a section when you need it.
01What Is SMC-L?
What the benefit pays for, and what it does not require.
SMC-L pays a higher monthly amount than the basic 100% rate, because the law recognizes that some service-connected disabilities cause needs beyond what a schedular rating compensates, specifically the need for daily care, the loss of certain functions, or specific anatomical losses.
You do not need a 100% rating to qualify. Under 38 U.S.C. § 1114(l) and 38 CFR § 3.350(b), eligibility turns on the functional need for regular aid and attendance (the § 3.352(a) factors), being permanently bedridden, or the listed anatomical losses. It is not a rating percentage you climb to.
SMC-L sits at the bottom of the L-through-T ladder. Higher tiers (SMC-M, N, O, P, R-1, R-2, T) require additional or more severe conditions, often combined.
02Five Paths to Qualify
Five separate circumstances, with distinct evidence needs.
A veteran qualifies for SMC-L by meeting any one of the following (see 38 CFR § 3.350(b)):
- Regular aid and attendance. Service-connected disabilities require help with activities of daily living. Most common path.
- Permanently bedridden. Service-connected disabilities require the veteran to remain in bed.
- Anatomical loss or loss of use of both feet (or amputation thereof).
- Anatomical loss or loss of use of one hand and one foot.
- Blindness in both eyes with visual acuity of 5/200 or less.
Each path has its own evidence pattern, examined below.
03The Aid & Attendance Criteria (§ 3.352(a))
Personal functions, daily safety, and regular assistance.
The most common SMC-L path is "regular aid and attendance." The legal criteria live in 38 CFR § 3.352(a). The veteran must, due to service-connected disability, meet at least one of these:
- Inability to dress or undress without assistance, or to keep ordinarily clean and presentable.
- Frequent need of adjustment of any special prosthetic or orthopedic appliance which by reason of the particular disability cannot be done without aid (this does not include adjustment of appliances which normal persons would be unable to adjust without aid).
- Inability to feed self through loss of coordination of upper extremities or through extreme weakness.
- Inability to attend to the wants of nature.
- Incapacity, physical or mental, which requires care or assistance on a regular basis to protect the veteran from hazards or dangers incident to their daily environment.
Not every listed factor must be present. The personal functions the Veteran cannot perform are considered together with the whole condition and the actual need for regular assistance.
04Permanently Bedridden
The requirement to remain in bed.
"Bedridden" under § 3.352(a) means the veteran's service-connected disability "actually requires that he or she remain in bed." Voluntarily remaining in bed, or prescribed bed rest for recovery, is not enough by itself. See the regulation for the full standard.
Bedridden status almost always overlaps with the regular A&A criteria above, so most veterans qualify on the easier A&A path. Bedridden is mainly relevant when documenting permanence (e.g., for SMC-O or higher).
05Anatomical Loss / Loss of Use
A functional standard, not a diagnosis alone.
"Loss of use" of a foot or hand is defined at 38 CFR § 3.350(a)(2):
"Loss of use of a hand or a foot will be held to exist when no effective function remains other than that which would be equally well served by an amputation stump at the site of election below elbow or knee with use of a suitable prosthetic appliance."
The legal test is functional, not anatomical. A veteran with a partially paralyzed foot from peripheral nerve injury can qualify if a prosthetic would serve them just as well as the remaining biological foot. Severe peripheral neuropathy, complete drop foot, or end-stage diabetic neuropathy commonly satisfy this standard.
The two qualifying combinations for SMC-L on this path:
- Both feet (loss or loss of use)
- One hand and one foot (loss or loss of use)
Loss of one foot alone, or one hand alone, qualifies for a different SMC level (SMC-K), not SMC-L.
06Blindness in Both Eyes (5/200 or Less)
Clinical measurements and the SMC-L threshold.
Visual acuity of 5/200 or worse in both eyes, with corrective lenses, qualifies for SMC-L under § 3.350(b)(2). Acuity is measured using the standard Snellen or equivalent test.
Note that "5/200" is the SMC-L threshold described above. Other vision-related criteria and disability combinations are addressed at higher levels. See the SMC-M guide and 38 CFR § 3.350 for those distinct criteria.
07Illustrative Example
A fictional scenario to illustrate the guidance.
Fictional example, not a real claimant. Names and facts are invented to show how the criteria above could apply in a single case.
Linda R. is a 78-year-old Navy veteran with service-connected COPD rated 100% and Parkinson's disease secondary to Agent Orange exposure. Over the past three years her Parkinson's has progressed to the point where she cannot safely bathe, dress, or prepare meals without her daughter's help every day. Her treating neurologist signed VA Form 21-2680 confirming she needs the regular aid and attendance of another person. Linda qualifies for SMC-L at $4,900.83 per month because she meets the aid-and-attendance criterion in 38 CFR § 3.352(a).
082026 Monthly Rate
Reference amounts, dependents, and replacement-rate basics.
SMC-L's 2026 monthly rate (single veteran, no dependents) is $4,900.83, set by VA each December 1 alongside the COLA-adjusted compensation rates. Dependents add a small supplement. A married veteran with one parent depending on them receives more.
This compares to:
- Schedular 100% (single, no dependents): $3,938.58
- SMC-K (loss-of-use add-on): adds $139.87 on top of the underlying rate
- SMC-L (this level): $4,900.83
- SMC-M: $5,408.55
So SMC-L is roughly $962/month above schedular 100%, about $11,500/year more than 100% schedular alone.
Use the VA Math Calculator to model SMC-K and SMC-S into your combined rating. SMC-L is the rate replacing your schedular amount.
09Evidence That Wins
Clinical findings, daily tasks, care plans, and supporting statements.
The single most-decisive piece of evidence for SMC-L A&A claims is VA Form 21-2680, Examination for Housebound Status or Permanent Need for Regular Aid and Attendance. The form is completed by a physician (VA or private), documenting which of the § 3.352(a) criteria the veteran meets and why.
Beyond Form 21-2680, supporting evidence patterns from BVA grants:
- Statements from caregivers describing exactly which daily tasks the veteran cannot perform unaided (specific, not generic).
- Home-health-agency assessments and care plans documenting the level and frequency of services provided.
- Treating physician letters explicitly addressing the § 3.352(a) criteria one by one. Generic "needs help with daily activities" statements are weaker than "patient cannot dress without assistance because of severe hand tremor secondary to service-connected Parkinson's."
- Records of falls, ER visits, or supervised wandering for the "incapacity requiring care to protect from hazards" criterion.
- Pharmacy records showing medication-management complexity (10+ medications, multiple times per day, with cognitive limitations preventing self-administration).
For loss-of-use paths, the decisive evidence is electromyography (EMG), nerve conduction studies, or orthopedic exam findings showing that "no effective function remains."
For blindness, an ophthalmology report with explicit Snellen acuity readings (or field-defect measurements) is required.
10SMC-L vs SMC-S (Housebound)
Different criteria. Different basic monthly rates.
SMC-S, sometimes called "housebound benefits," sits below SMC-L on the ladder. Veterans often confuse the two. The difference:
SMC-S (Housebound)
Statute: 38 USC § 1114(s)
Reg: 38 CFR § 3.350(i)
Qualifies if: 100% rated for one disability AND either (a) substantially confined to home, OR (b) has additional disabilities rated 60% or more separately.
Pays less than SMC-L. The SMC-S basic monthly rate replaces the regular compensation rate.
SMC-L (Aid & Attendance)
Statute: 38 USC § 1114(l)
Reg: 38 CFR § 3.350(b)
Qualifies if: Need regular A&A, permanently bedridden, anatomical loss/loss of use of both feet or one hand and one foot, or legally blind.
Pays substantially more than SMC-S. Replaces the schedular rate entirely.
If a veteran arguably meets both, SMC-L is the better award. VA does not pay both at the same time, the higher rate controls.
11SMC-L When You're on TDIU or Rated Under 100%
The functional need, not a rating percentage alone.
This is one of the most misunderstood points in SMC, including, until recently, on this site. SMC-L does not require a 100% schedular rating. Under 38 USC § 1114(l) and 38 CFR § 3.350(b), eligibility turns on the functional need for regular aid and attendance (the § 3.352(a) factors), permanent bedridden status, or the listed anatomical losses, never on a rating percentage.
- TDIU veterans qualify directly. A veteran paid at the TDIU rate, or rated at a schedular level below 100% (say 70%), can receive SMC-L if service-connected disabilities create the need for regular aid and attendance.
- It is a straight SMC-L claim. It does not run through SMC-T (that is the separate benefit for traumatic brain injury), and it does not need the Bradley v. Peake single-disability rule (that rule bridges TDIU to the 100% predicate that SMC-S requires. SMC-L has no such predicate).
- The need must come from service-connected disabilities. Aid and attendance required because of a non-service-connected condition does not count.
- SMC-L replaces your current rate. The 2026 SMC-L rate ($4,900.83) is higher than the 100% or TDIU rate ($3,938.58). It is paid instead of, not on top of, the underlying compensation.
Evidence is the same as any SMC-L A&A claim: a VA Form 21-2680 completed by a physician documenting the § 3.352(a) criteria. See Evidence That Wins and the A&A Exam Guide.
12How to File
Forms, supporting records, and examination preparation.
- File VA Form 21-526EZ (Disability Compensation and Related Compensation Benefits) and identify the SMC-L claim. SMC can be claimed on this same form even if you're already 100%.
- Submit VA Form 21-2680 completed by a physician documenting the § 3.352(a) criteria. This is the single most important piece of evidence.
- Attach supporting evidence: caregiver statements, treatment records, home-health assessments. The more specific the language matching § 3.352(a), the stronger.
- Expect a VA exam (Aid & Attendance examination, sometimes called an A&A exam). See the A&A Exam Guide for what the examiner looks for and how to prepare.
If denied, the appeal options under the Appeals Modernization Act are Higher-Level Review, Supplemental Claim, or appeal to the Board (Direct Review or Evidence docket). See Appeals Overview. See SMC Appeals Data for Board outcomes, recurring denial reasons, and evidence cited in appealed cases.
13Common Mistakes
Gaps to watch for when documenting the need.
- Filing without VA Form 21-2680. Without the form, VA will order an A&A exam. The A&A exam is often less detailed than what a treating physician would document on the form. Pre-empt the exam with a strong 21-2680.
- Using generic language. "Needs help with daily activities" is too vague. Match the exact § 3.352(a) language: "cannot dress without assistance," "cannot feed self due to hand tremor," "requires supervision to protect from hazards in daily environment."
- Confusing SMC-L with SMC-S. They have very different criteria and rates. If you qualify for SMC-L, do not settle for SMC-S.
- Not addressing service-connection of the underlying need. SMC-L only pays for needs caused by service-connected disabilities, not age-related needs. The 21-2680 should explicitly tie each impairment to a service-connected condition.
- Missing loss-of-use cases. Severe peripheral neuropathy from service-connected diabetes, near-complete drop foot from spinal injury, or end-stage joint disease often satisfies the "no effective function remains" test. These cases are routinely under-claimed.
- Forgetting field-of-vision blindness. Concentric contraction to 5° in both eyes qualifies, even with technically better acuity. See 38 CFR § 4.79.
A different way to take it in
Four guides to keep close.

Visual guide: SMC-L Aid and Attendance
The regulatory factors and the whole disability picture.
View full size
Visual guide: Aid and Attendance Evidence
Daily tasks, clinical findings, care frequency, and safety.
View full size
Visual guide: VA Form 21-2680 Guide
Connect diagnoses, limitations, and the assistance required.
View full size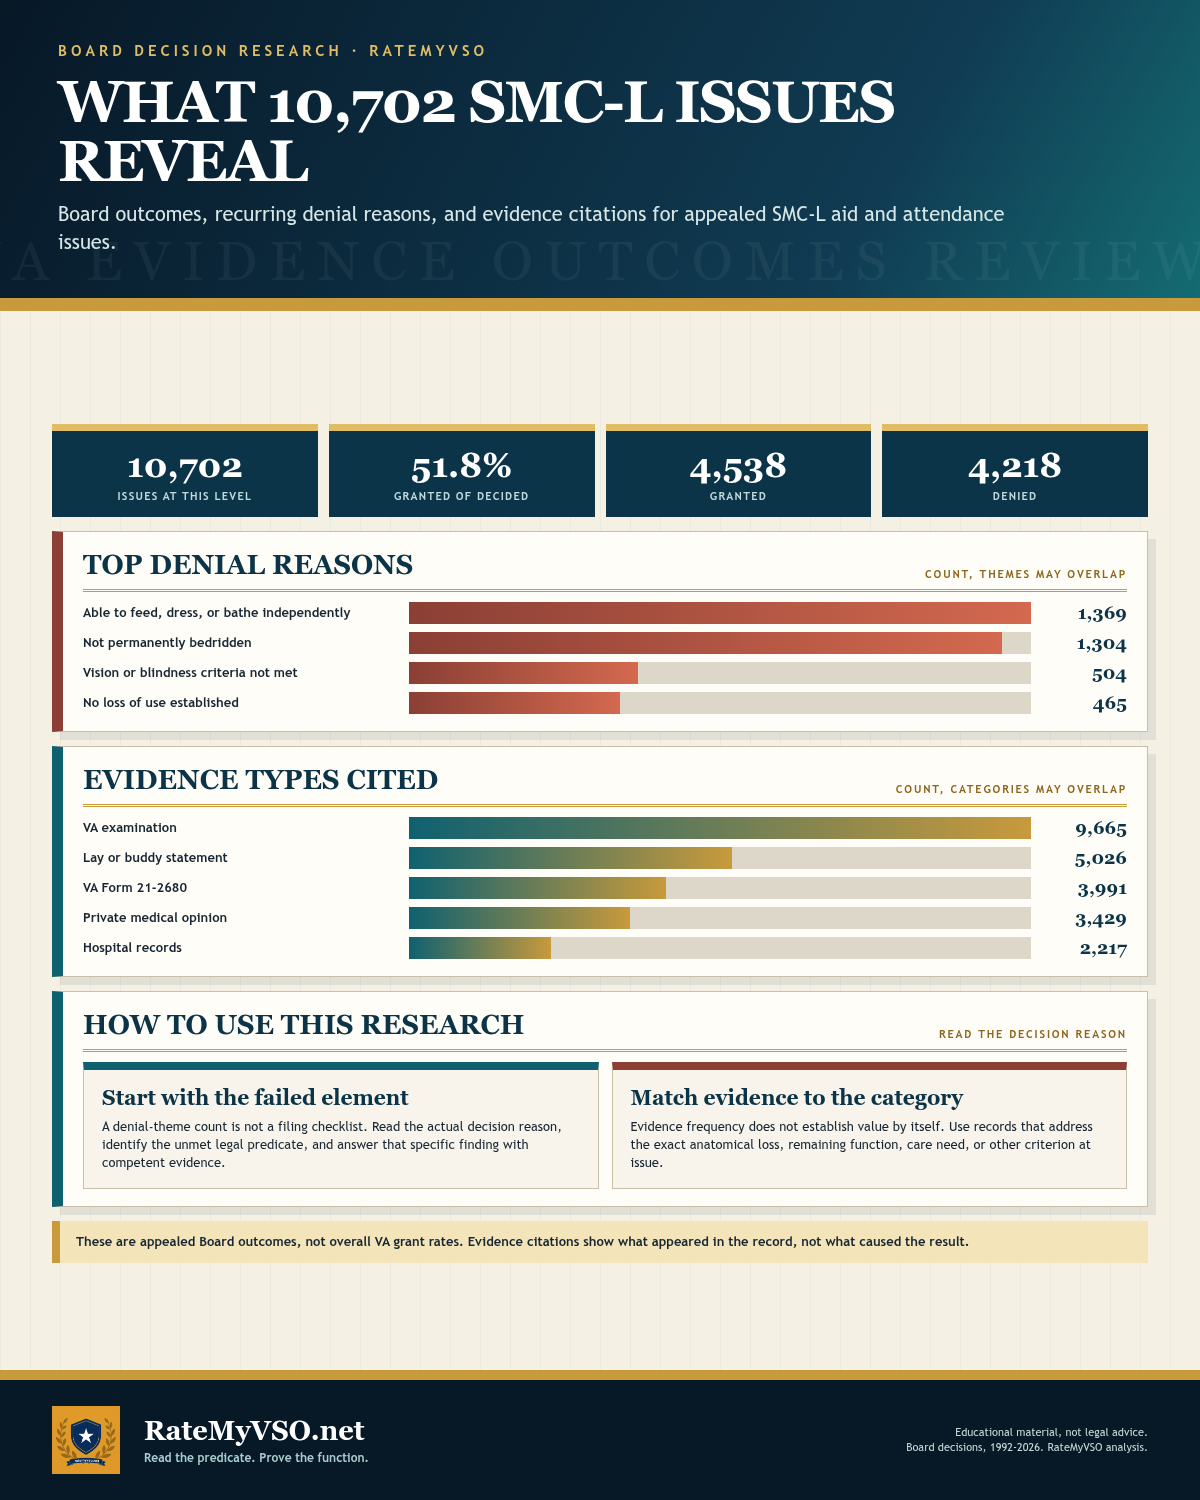
Visual guide: SMC-L Board Outcomes
The appealed record, named denial reasons, and cited evidence.
View full sizeThe published Board record
What the appealed cases show.
Patterns to understand, not odds for your own claim.

The live Board outcome figures for SMC-L appear here when they are available. They are also published on SMC Appeals Data.
This page is educational and is not legal advice. For help with an SMC claim, work with a VA-accredited representative.